
Clinical Data Collection: CRF Design, EDC, Process & Data Quality

Clinical research draws data from many sources, including study visits, laboratories, electronic health records, patient-reported outcomes, imaging systems and connected devices. However, more data does not necessarily mean better evidence. Poorly defined variables or inconsistent data capture can affect the quality of the final dataset.
Clinical data collection translates protocol requirements into structured data that can be reviewed, validated and analysed. Therefore, clear data definitions, appropriate collection methods and consistent procedures are essential for producing reliable research evidence.
In short, what is clinical data collection if not the disciplined process of turning protocol requirements into evidence that can withstand scrutiny?
Recommended:
Explore Comprehensive Site Management Solutions for Clinical Research
The Protocol Is Where the Data Requirements Begin
A clinical trial starts with a protocol, which defines what the study aims to investigate, who will participate, what outcomes will be measured and when assessments will take place. These requirements are then converted into specific data fields for collection. For example, a hypertension study may need blood-pressure readings, treatment details, laboratory results, medication use and adverse events at defined study visits. Each item must have a clear definition and, where relevant, a specified unit, response format and collection time.
Consistent clinical data in clinical trials starts with protocol-driven field definitions rather than convenience of data entry.
This step is important because the quality of the final dataset depends on collecting the right information in a consistent way. Collecting unnecessary data increases workload, while missing an important variable can limit the study’s ability to answer its research question. CDISC’s CDASH framework supports standardised clinical data collection by helping define and organise data consistently and maintain traceability into later stages such as SDTM. The basic principle is that data should be designed around the study objectives and protocol requirements, rather than simply around what is easiest to enter into a database.
| Protocol requirement | Collection specification | Example |
| Efficacy endpoint | Define measurement and timing | Blood pressure at specified visits |
| Safety monitoring | Define event fields and assessment | Adverse event, severity, onset |
| Treatment exposure | Capture dose and administration | Dose, frequency, start/end date |
| Eligibility | Define required baseline information | Laboratory or clinical criteria |
| Follow-up | Specify assessment window | Scheduled post-treatment assessment |
CRF Design Determines What the Database Can Actually Know
The case report form (CRF), or its electronic equivalent, is the practical interface between the protocol and the clinical database. A well-designed CRF does more than provide blank fields. It determines how clinical concepts are converted into structured data.
CDISC recommends standardised question text, appropriate response mechanisms and consistent terminology. For example, where a binary response is expected, a defined Yes/No structure can avoid the ambiguity created when an unchecked field could mean either “No” or “not completed.” CDISC also emphasises that collection standards should support semantic interoperability and traceability.
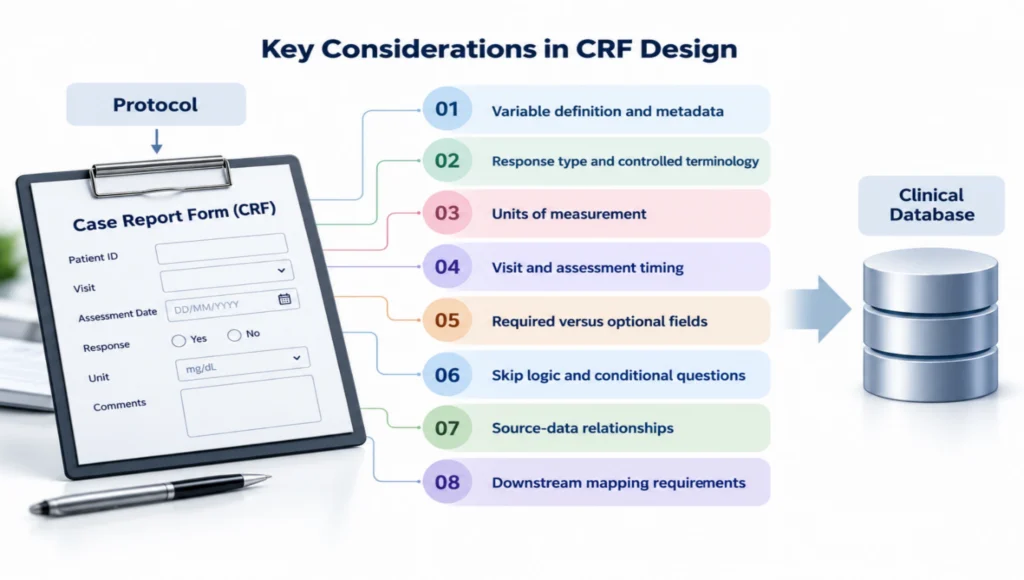
This is one reason CRF development involves more than clinical staff alone. Data managers, statisticians, programmers and other study functions may need to contribute because decisions made at collection can affect later database design, analysis and regulatory submission.
One Patient Visit Can Generate a Chain of Linked Data
In a Phase II hypertension trial, a patient visit may generate blood-pressure readings, medication details, laboratory results and adverse-event information. These observations move from source records to the eCRF, where automated checks can identify missing or inconsistent entries. The workflow is illustrated in the figure below.
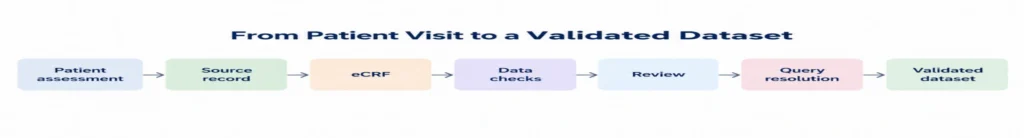
If an entered value differs from the source record, the study team investigates and resolves the discrepancy according to the study procedures. This is where data collection connects with data management—ensuring that captured information is accurate, complete and traceable.
This distinction is important: data capture records an observation; data management establishes whether that observation is sufficiently complete, consistent and traceable for its intended use.
Validation Rules Catch Problems Before They Become Analysis Problems
Clinical data is checked for more than missing fields. Electronic systems can flag problems such as unusual values, conflicting dates, duplicate records or information that does not match the original patient record.
| Check | What it identifies |
| Missing data | Required information has not been entered |
| Unusual value | A result falls outside the expected range |
| Conflicting information | Two fields contain inconsistent details |
| Date error | Events appear in an incorrect sequence |
| Duplicate record | The same information may have been entered twice |
| Source mismatch | Entered data differs from the original record |
A flagged entry does not always mean the data is wrong. It signals that someone needs to review it. For example, an unusually high laboratory result may be clinically valid, while a different value from the patient record may require clarification. Automated checks find potential problems; trained study staff determine what they mean and resolve them appropriately.
EDC Software Is Becoming the Operating Layer for Study Data
Electronic Data Capture (EDC) systems have replaced much of the paper-based data entry used in clinical research with structured digital workflows. Platforms such as Medidata Rave and Oracle Clinical One support electronic study-data capture, review and related data-management activities.
An EDC system is more than a digital form. It brings together several functions that help study teams collect and manage clinical information consistently, as illustrated in the figure below.
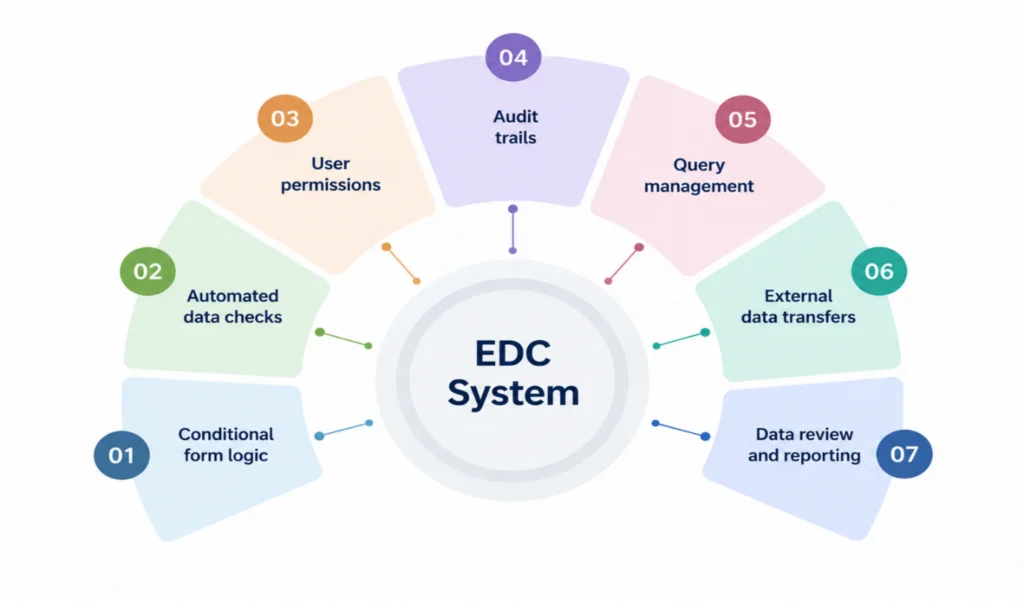
These functions help reduce manual errors, identify potential data problems early and maintain controlled access to study information. The software provides the technical environment, while the study protocol determines what needs to be collected and how the information should be managed.
Clinical Research Data Now Comes From Multiple Sources
Clinical studies increasingly combine data from multiple digital and clinical sources:
- Electronic Health Records (EHRs): Provide relevant clinical information from routine healthcare records.
- Electronic Data Capture (EDC): Captures structured study data through digital research workflows.
- Laboratory and imaging systems: Provide test results and clinical measurements.
- Electronic Patient-Reported Outcomes (ePRO): Capture symptoms, treatment experiences and other participant-reported outcomes.
- Wearable and connected devices: Generate repeated measurements between scheduled study visits.
Different systems may use different formats, identifiers, units or definitions. Standardised terminology, clear source information and consistent data structures are therefore essential for maintaining data quality and traceability. In India, clinical-trial activities operate within the regulatory framework of the New Drugs and Clinical Trials Rules, 2019, administered by the Central Drugs Standard Control Organisation (CDSCO).
Recommended:
How Field Data Collection Enhances Clinical Studies
Electronic Health Records, Remote Monitoring and Artificial Intelligence Are Reshaping Data Capture
Clinical research is moving beyond information collected only during scheduled research-site visits. Several technologies are contributing to this shift:
- Electronic Health Record (EHR) integration can reduce repeated manual entry by transferring relevant healthcare information into research workflows.
- Remote monitoring can capture patient information outside traditional study-site visits.
- Electronic Patient-Reported Outcomes (ePRO) allow participants to report symptoms, treatment experiences and other outcomes digitally.
- Connected devices and wearables can provide repeated measurements between scheduled visits.
- Artificial Intelligence (AI) is being explored to identify unusual records, support data review and prioritise potential discrepancies.
AI should support trained research and data-management teams rather than independently determine whether clinical information is correct. As these technologies expand, clinical datasets are becoming increasingly digital, continuous and multi-source, making integration and quality control more important.
Robust clinical data collection in healthcare settings increasingly depends on EDC platforms that unify information from EHRs, laboratories and wearables.
Data Quality Is Built Before Statistical Analysis
A reliable analysis dataset is the result of decisions made throughout the study, beginning with the protocol and continuing through data collection and review.
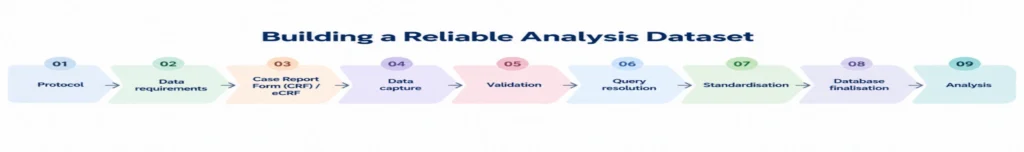
When each stage is properly designed, researchers can determine what was collected, where it came from, whether it is reliable and how it was prepared for analysis. The goal is therefore not simply to collect more data, but to produce information that is accurate, consistent, traceable and fit for the research purpose.
Conclusion
Clinical data collection is the point at which a research protocol becomes measurable evidence. Its quality depends on much more than accurate data entry; it requires carefully defined variables, fit-for-purpose CRFs or eCRFs, validation rules, controlled terminology, appropriate technology and traceability across data sources. As EHR integration, remote monitoring, ePRO, digital health technologies and AI-assisted workflows expand, clinical research organisations will increasingly need to manage not only the volume of data but also its context, provenance and interoperability. A well-designed collection process ultimately gives researchers a dataset that can be examined, validated and trusted.
Ultimately, disciplined clinical data collection determines whether a dataset can hold up to scientific and regulatory scrutiny.
Build a Stronger Clinical Research Data Workflow
Reliable research depends on reliable data from the first collection point onward. Simbi Labs supports clinical and healthcare research projects with structured data collection, data management, validation, statistical analysis and research support.
Book a free consultation or contact Simbi Labs at grow@simbi.in to discuss your research requirements.
FAQs
What is the difference between CRF and eCRF?
A CRF is the study instrument used to capture protocol-required participant information. An eCRF is its electronic implementation within a clinical data-capture environment, typically providing additional functions such as edit checks, audit trails and electronic query workflows.
What is CDASH in clinical research?
CDASH is a CDISC standard for structuring and standardising clinical-trial data collection. It helps make collected information more consistent and supports traceability into downstream standards such as SDTM.
Why are edit checks important in EDC systems?
Edit checks identify potential missing, inconsistent, implausible or conflicting information while data are being managed. They reduce the need to discover every discrepancy only after the study dataset has been assembled.
What is changing in clinical data collection?
Clinical research is increasingly incorporating EHR integration, electronic patient-reported outcomes, remote and digital health technologies, external data sources and AI-assisted review. ICH E6(R3) explicitly recognises modern data sources and technologies within a quality-focused clinical-trial framework.